Independent Evidence Desk · Educational reference only; not medical advice. Not affiliated with USPSTF, AHRQ, or ACS. Symptomatic patients require diagnostic workup, not routine screening.ISSN-LREF · 2026.11
Cancer Screening Guidelines by Age: Read the 1,000-Person Numbers
Why does the U.S. Preventive Services Task Force (USPSTF) recommend biennial mammograms starting at age 40, while the American Cancer Society (ACS) recommends annual screening at 45 and the UK NHS begins at 50? Why is an annual stool FIT test often safer than a multi-target DNA test for avoiding surprise diagnostic co-pays?
Mainstream health portals repeat relative percentages without denominators. This reference desk places federal and specialty guidelines side by side and translates every trial into 10-year absolute outcomes per 1,000 asymptomatic adults screened.
Clinical Summary & Absolute Outcome Takeaway
Routine population screening reduces cancer-specific mortality in average-risk adults for four core organ sites: cervical (ages 21 to 65), colorectal (ages 45 to 75), breast (ages 40 to 74), and lung (ages 50 to 80 with a 20 pack-year smoking history). When medical societies recommend different starting ages or intervals, they are weighing a 1 to 5 per 1,000 mortality reduction against 100 to 500 false-positive recalls.
Clinical Gate (Screening vs. Diagnostic Workup): Screening protocols apply strictly to asymptomatic adults. If you have a palpable breast lump, rectal bleeding, persistent hemoptysis, unexplained weight loss, or iron-deficiency anemia, skip population screening tables and request an immediate diagnostic evaluation.
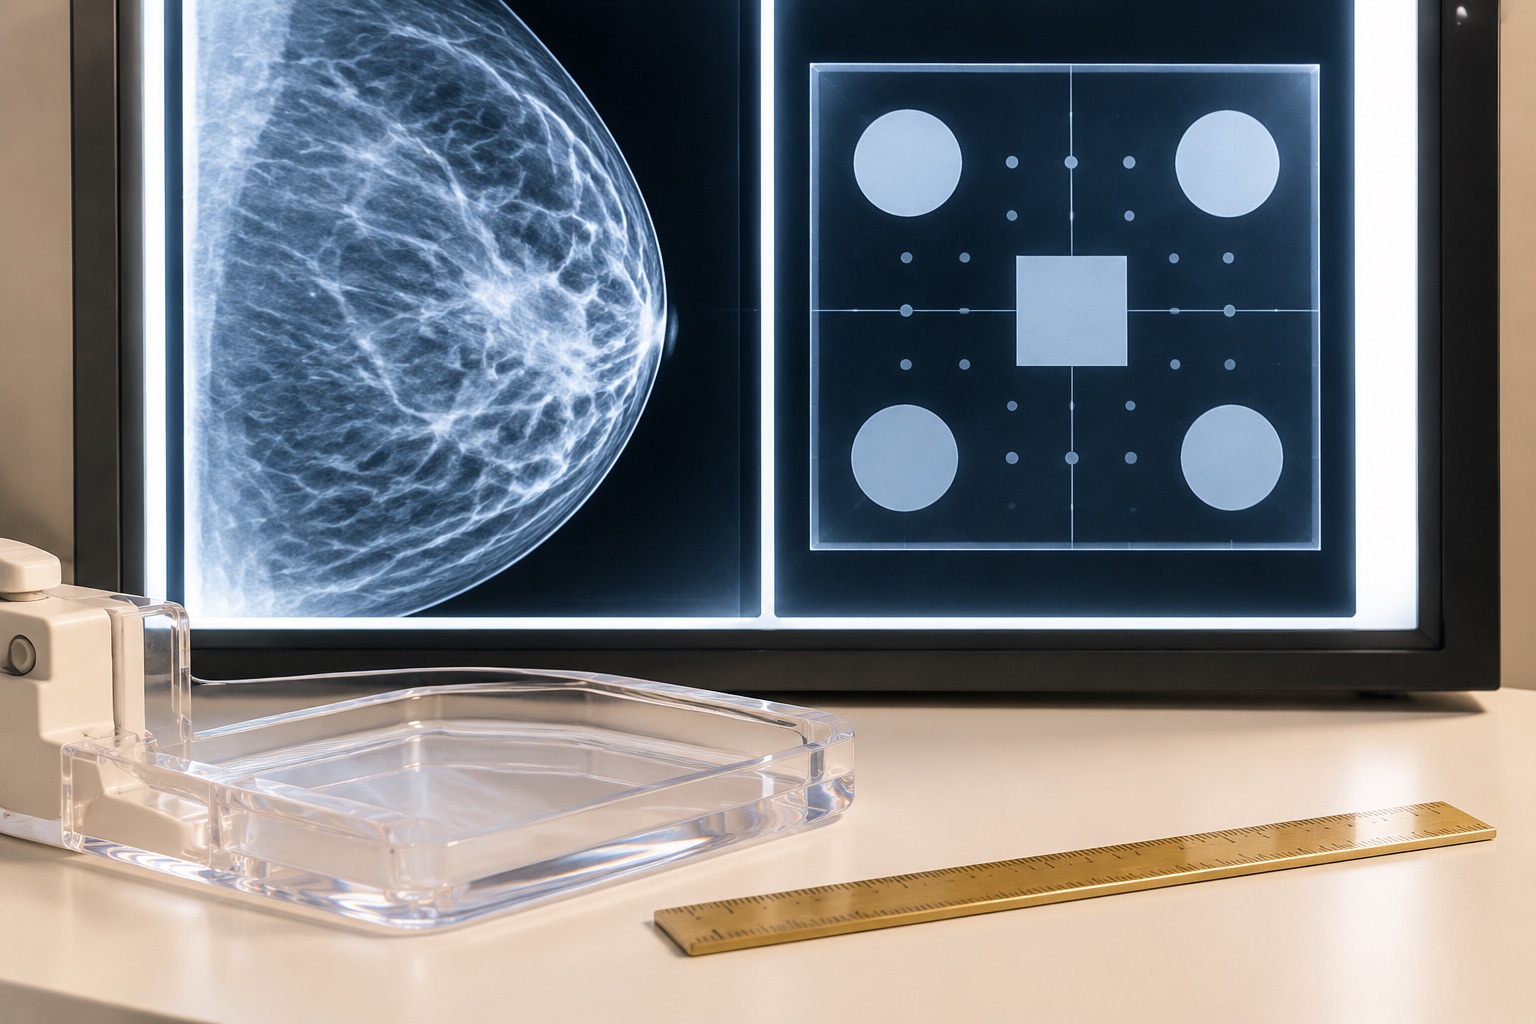
PLATE 01 · DIGITAL BREAST TOMOSYNTHESIS & PHANTOM CALIBRATIONUSPSTF GRADE B (AGES 40-74)
2015-2026 Archival Lineage: Cited by Harvard Medical School (health.harvard.edu) during the 2015 USPSTF vs. ACS mammography guideline debate. Maintained as a non-commercial multi-society concordance reference.
Interactive Device 01 · Select Your Age Band for Society Concordance
Ages 21 to 29: Cervical Cytology Only for Average-Risk Adults
USPSTF GRADE A
For asymptomatic adults aged 21 to 29 without hereditary syndromes (such as BRCA1/2 or Lynch syndrome), cervical screening is the sole evidence-backed population cancer screen. USPSTF recommends cervical cytology (Pap test) every 3 years starting at age 21, whereas the ACS prefers initiating primary HPV testing at age 25.
Ages 30 to 39: Transition to Primary High-Risk HPV Testing
USPSTF GRADE A
Between ages 30 and 39, primary high-risk HPV testing every 5 years (or co-testing every 5 years, or cytology alone every 3 years) carries a Grade A recommendation. Routine mammography, PSA, and multi-cancer blood tests are not recommended for average-risk individuals in this decade, though formal lifetime breast risk assessment should occur by age 30 for women with dense tissue or family history.
GRADE B Start at age 40, biennial screening every 2 years (updated 2024 from 2016 Grade C).
Optional start at 40-44; mandatory annual mammography starting at age 45.
Starting at 40 vs. 50 prevents ~1.5 additional breast cancer deaths per 1,000 women, accompanied by ~520 false-positive recalls and ~62 benign biopsies.
GRADE A Primary hrHPV test every 5 years (or Pap every 3 years).
Primary hrHPV test every 5 years preferred through age 65.
Reduces invasive cervical cancer mortality by >80% compared with unscreened cohorts.
Ages 50 to 64: Peak Net Benefit Window Across All Four Core Screenings
COLON: GRADE ABREAST & LUNG: GRADE B
Ages 50 to 64 represent the highest absolute mortality reduction per 1,000 people screened: colorectal screening upgrades to USPSTF Grade A, biennial mammography continues (Grade B), low-dose CT lung screening begins at age 50 for adults with a 20 pack-year smoking history (Grade B), and PSA testing enters shared decision-making at age 55 (Grade C).
Ages 65 to 74: Cervical Exit Rule at 65 & Continued Colon/Breast/Lung Screening
COLON & BREAST ACTIVE
At age 65, cervical screening can safely stop (Grade D to continue) if the patient has 3 consecutive negative Pap tests or 2 consecutive negative HPV tests within the past 10 years and no history of CIN2+. Breast mammography continues through age 74, colorectal through age 75, and lung LDCT through age 80 for eligible smokers.
Age 75 and Older: Competing Mortality & Stopping Rules
INDIVIDUALIZED / EXIT
Because cancer screening requires a 7- to 10-year lag time before survival curves separate, routine screening after age 75 (or when life expectancy is under 10 years) exposes patients to immediate procedural harms (colonoscopy perforation, overdiagnosis surgery) with diminishing survival benefit. Colorectal screening is Grade C from 76 to 85 and Grade D after 85; PSA is Grade D at age 70+.
Signature Device 02 · Harding Center Risk Literacy Standard
The 1,000-Person 10-Year Absolute Outcome Ledger
Relative risk reductions (such as "reduces mortality by 20%") obscure baseline probability. Below is what happens when 1,000 average-risk adults undergo 10 years of guideline-concordant screening across the four major modalities.
Biennial Screening Mammography (Women Aged 50 to 69 Over 10 Years)
COHORT: 1,000 ASYMPTOMATIC WOMEN · 10-YEAR HORIZON
5.0 → 4.0
Breast Cancer Deaths
Drops from ~5 per 1,000 unscreened to ~4 per 1,000 screened (~1 life saved over 10 yrs).
996 / 1,000
Do Not Die of Breast Cancer
Whether screened or unscreened, 995 of 1,000 women do not die from breast cancer in 10 years.
~420 / 1,000
False-Positive Recalls
Experience at least one abnormal mammogram requiring callback imaging; ~55 undergo benign biopsy.
~3 to 4 / 1,000
Overdiagnosed Cancers
Diagnosed and treated for slow-growing DCIS or invasive tumors that would never have caused symptoms.
~150-300 incidentaloma findings on whole-body MRI; ~62% of positive MCED signals require diagnostic cascades
Organ Dossiers & Evidence Audits
Explore Clinical Screening Dossiers by Modality
Each organ dossier examines why guidelines diverge, how to avoid preventive-to-diagnostic insurance billing traps, and when supplemental imaging is warranted.
Breast Cancer: Age 40 vs. 45 vs. 50 & Dense Tissue
USPSTF GRADE B
Why the USPSTF lowered its routine mammography starting age from 50 back to 40 in 2024, how 3D digital breast tomosynthesis lowers recall rates, and what the 2024 FDA national breast density notification rule means for BI-RADS Category C and D patients.
Core Modality
Biennial 2D/3D Digital Mammography (Ages 40-74)
Key Contention
Supplemental MRI vs. Ultrasound in Category D Extremely Dense Breasts
Colorectal Cancer: Colonoscopy vs. FIT vs. Cologuard
USPSTF GRADE A (50-75)
A head-to-head comparison of 10-year colonoscopy, annual fecal immunochemical testing (FIT), and 3-year multi-target stool DNA (Cologuard), including the 10% to 13% false-positive rate and the federal preventive-to-diagnostic co-pay rule.
Core Modality
10-Yr Optical Colonoscopy or Annual Immunochemical FIT (Ages 45-75)
Key Contention
Stool DNA specificity drop in older adults and polyp removal coding
Includes an interactive pack-year calculator comparing the USPSTF 15-year quit-time cutoff against the 2023 ACS guideline (which eliminated the quit-year cap), plus benign rates for Lung-RADS Category 2 and 3 pulmonary nodules.
Plain-language answers grounded in USPSTF, ACS, and 1,000-person cohort data.
Why do the USPSTF and the American Cancer Society disagree on mammogram starting ages?
Both organizations evaluate the exact same clinical trial data and CISNET microsimulation models, but they assign different weights to harms versus benefits. The ACS prioritizes maximizing total lives saved (recommending annual initiation at 45 and optional at 40), whereas the USPSTF balances mortality reduction against cumulative false-positive recalls, benign core biopsies, and overdiagnosis across a 34-year screening span, leading to its 2024 Grade B recommendation for biennial screening from age 40 to 74.
Which cancer screenings are 100% covered without co-pay under U.S. health insurance?
Under Section 2713 of the Affordable Care Act (ACA), private non-grandfathered health plans and Medicare must cover any screening test that holds a USPSTF Grade A or Grade B recommendation with zero patient deductible or co-pay. This covers cervical screening (ages 21 to 65), colorectal screening (ages 45 to 75), biennial mammography (ages 40 to 74), and annual low-dose CT lung screening (ages 50 to 80 with 20 pack-years).
Can a multi-cancer early detection (MCED) blood test replace my colonoscopy or mammogram?
No. Current cell-free DNA methylation blood tests have low sensitivity for Stage I cancers (often 16% to 30% in early-stage breast and colorectal lesions) and cannot detect precancerous colonic polyps or cervical dysplasia before they turn malignant. Medical societies unanimously warn that a negative MCED blood test must never delay routine Grade A or Grade B screening.